Running a clinical trial today means coordinating dozens of research sites, thousands of patient visits, and millions of individual data points, all under regulatory scrutiny that grows stricter every year. A phase III protocol now collects an average of 5.9 million data points, a figure climbing 11% annually since 2020, according to Tufts Center for the Study of Drug Development. Spreadsheets and disconnected tools were never built for that scale.
A clinical research management system provides sponsors, CROs, and research teams with a single platform to plan studies, track patient enrollment, manage documents, and monitor trial performance in real time. This guide walks through what these platforms do, how they improve clinical trial efficiency and compliance, and where the technology is heading. By the end, you will know how to judge whether a CRMS fits your research operations and what separates a strong implementation from a stalled one.
What a Clinical Research Management System Actually Does
People use several names for the same category of software: clinical research management system and clinical trial management system (CTMS). Whatever the label, the job stays consistent.
A CTMS differs from the tools it sits beside. An electronic data capture (EDC) system records the clinical data collected during patient visits. An electronic trial master file stores regulatory documents. The CTMS connects to both and adds the operational layer on top: who is enrolled where, which sites are behind schedule, how the budget is tracking, and what needs attention this week.
“The CTMS system is where you check upcoming site visits, trip reports, and protocol deviations.”
Tiffany Ashton, ClinEssentials
CRMS vs. CTMS vs. EDC vs. eTMF
Each system owns a different layer of the same trial, and the separation is deliberate. Operational status, patient data, and regulatory documents stay apart so that access rights and audit trails hold up under inspection. Problems start when a team expects one system to cover another one's job:
|
System |
What it manages |
Who works in it daily |
|
CRMS |
Umbrella term for the operational platform. Most vendors use it interchangeably with CTMS, though at the site level it often stretches to study feasibility and staff workload |
Site directors, research administrators |
|
CTMS |
Trial operations: enrollment status, site activation, monitoring visits, milestones, budgets, and site payments |
Clinical operations managers, coordinators, finance |
|
EDC |
Patient-level clinical data from visits: case report forms, edit checks, and data queries |
Data managers, coordinators, monitors |
|
eTMF |
Essential regulatory documents: protocols, contracts, ethics approvals, signatures, and version history |
Regulatory affairs, quality assurance, sponsors |
A single study runs these layers side by side, with the CTMS acting as the hub that pulls status from the EDC and the eTMF into one operational view.
Core capabilities you can expect from a CTMS
Most CTMS platforms cover a recognizable set of capabilities, though the depth varies by vendor and by whether the system is built for a single site or an enterprise sponsor running multiple studies at once.
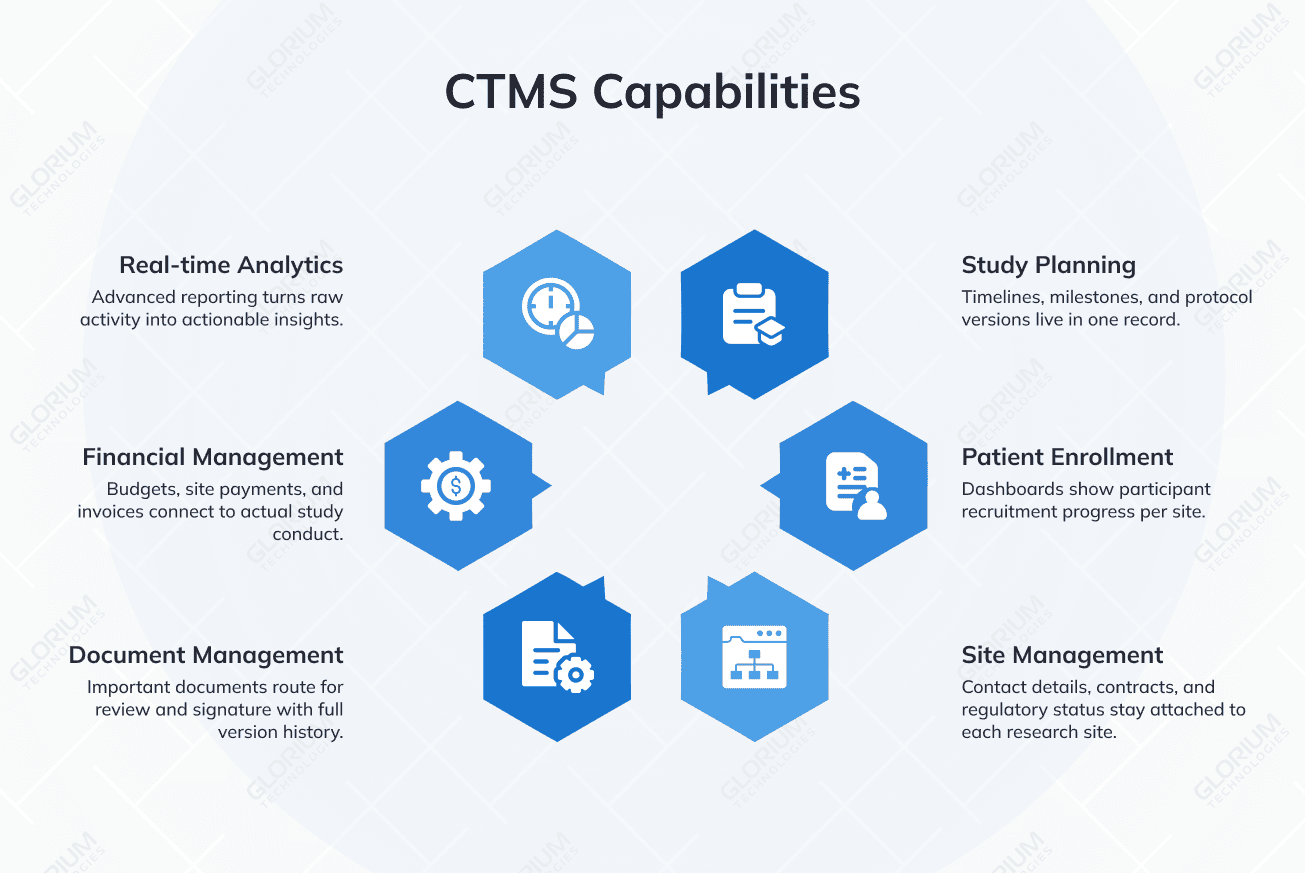
- Study planning and tracking: Timelines, milestones, and protocol versions live in one record, so the study team works from up-to-date information rather than chasing email threads
- Patient enrollment and recruitment: Dashboards show participant recruitment progress per site, flagging studies that risk missing targets early enough to act
- Site and investigator management: Contact details, contracts, regulatory status, and monitoring visit history stay attached to each research site
- Document and protocol management: Important documents route for review and signature with full version history
- Financial management: Budgets, site payments, and invoices connect to actual study conduct, giving finance teams a real picture of spend
- Real-time trial analytics: Advanced reporting turns raw activity into actionable insights for clinical operations managers
What ties these together is the audit trail. Every change to a record carries a timestamp and a user’s name, which matters when an FDA or EMA inspector asks who modified a patient record and when. That single feature is often the difference between a clean audit and a finding.
Why Research Teams Are Moving Away from Manual Processes
A 2025 TransCelerate and Tufts CSDD study found that phase III protocols now average 5.96 million data points, and the same research showed that up to 32.5% of patient data comes from procedures that do not support primary or key secondary endpoints. The same Tufts CSDD research urged sponsors to lean harder on data management strategies, like real-time interim assessment and automation, since legacy data collection habits no longer scale. Stronger data management also protects patient safety because exclusionary lab values get flagged for review instead of being buried in a spreadsheet. More data, more sites, and more procedures mean manual processes buckle under the load. A coordinator who once tracked one study in a spreadsheet now juggles several, each with its own enrollment targets and reporting cadence.
The financial stakes sharpen the point. The direct cost of running a phase III trial was estimated at roughly $55,700 per day, and the value of a single delayed day was about $500,000 in unrealized sales. When a trial slips because data sits in someone's inbox or a site activation stalls, the meter keeps running.
Here is how the two approaches compare across the work a clinical operations team handles every day:
|
Activity |
Manual processes |
Clinical research management system |
|
Patient enrollment tracking |
Spreadsheets updated by hand, often days behind |
Live dashboards with real-time data capture per site |
|
Document management |
Email chains and shared drives, version confusion |
Centralized eTMF with full audit trails |
|
Site payments |
Manual reconciliation, frequent disputes |
Payments tied to verified study conduct |
|
Regulatory reporting |
Pulled together under deadline pressure |
Generated on demand from current records |
|
Cross-team visibility |
Fragmented across tools and inboxes |
Single unified platform for the study team |
A clinical research management system produces more reliable data, which feeds directly into data quality and data integrity, the two things regulators scrutinize hardest. A study team that trusts its numbers spends less energy double-checking and more on the science.
Key Features to Weigh When Choosing a CTMS Solution
Choice of clinical trial management software is less about feature checklists and more about your workflow fit. Still, a few capabilities separate a serviceable CTMS solution from one that earns its keep across multiple studies.
Integration with your existing systems
The platform needs to exchange clinical data with your EDC system, sync with your electronic trial master file, and often connect to financial software and electronic patient-reported outcomes tools. Platforms that follow interoperability standards like HL7 and FHIR move data cleanly between other systems, which matters more as decentralized trials pull in feeds from remote patient monitoring devices and patient apps. Ask any vendor to show how their system has integrated with the specific tools you already run, not just a generic list of supported standards.
Reporting that drives decisions
Raw data helps no one. The value comes from advanced reporting that surfaces enrollment lags, budget overruns, and safety signals before they become crises. Strong CTMS software lets a study team build dashboards for different roles, so a regulatory affairs professional and a data manager each see what they need right away.
Security and a user-friendly interface
Patient data demands strict security, so any CTMS platform handling it should support HIPAA and GDPR compliance through role-based access and encryption. Security alone won't guarantee success, though, because adoption hinges just as much on a user-friendly interface. When clinical research teams find a system clumsy, they work around it, and those workarounds reintroduce the high risks the security features were meant to prevent. That tension is why your evaluation should weigh how the people doing daily data collection actually experience the tool, not just whether it checks the compliance boxes.
Common Challenges and How to Get Ahead of Them
No platform is plug-and-play, and pretending otherwise sets teams up for disappointment. The challenges are predictable, which means you can plan around them. The four that derail projects most often are:
- Complex system integration: Connecting a CTMS to legacy EDC systems, billing tools, and document repositories takes real engineering, especially when older systems lack modern APIs
- High implementation cost: Enterprise deployments carry licensing, configuration, and training expenses that can surprise smaller research organizations
- Data migration: Moving historical clinical data from spreadsheets or an aging system into a new platform is a time-consuming task, and rushing it risks corrupting the very data integrity the new system is meant to protect
- Training and adoption barriers: Even the best tool fails if the study team never fully learns it, so workarounds creep back in, and the platform sits half-used
Scope the integration work before signing anything, budget for migration and training as line items rather than afterthoughts, and pilot the system with one study before rolling it across multiple studies.
Where Clinical Trial Technology Is Heading
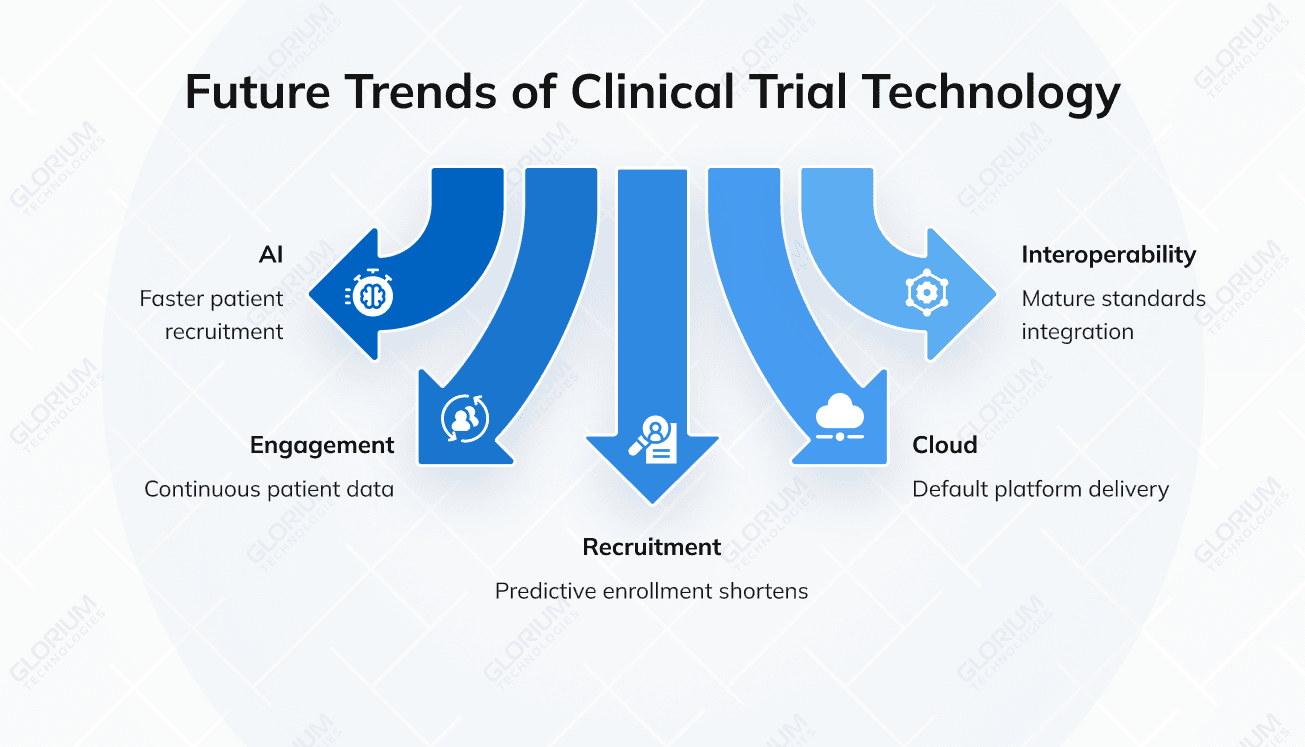
The next phase of clinical trial management is already taking shape, and most of it points toward more automation and less administrative burden on research staff. Five shifts stand out for teams planning their next platform investment.
AI implementation
AI-driven platforms now help with patient recruitment predictions, matching participants to studies faster than manual screening can. The technology is moving from experimental pilots into everyday clinical operations, where it flags eligible candidates and forecasts site performance before recruitment stalls. Fully digital and decentralized trials continue to spread, supported by real-time data monitoring systems that catch issues as they happen rather than at the next scheduled review.
Patient engagement gets continuous
Patient engagement is also shifting. Electronic patient-reported outcomes, social media platforms for recruitment, and remote patient monitoring are giving sponsors richer, more continuous data while easing the visit burden on participants. These changes raise the bar for what a CTMS needs to handle, which is why the platforms gaining ground are the ones built to absorb new data sources without a rebuild. A system that locks you into today's data feeds becomes a liability the moment your next protocol calls for something new.
Predictive recruitment shortens enrollment
Slow patient enrollment remains one of the most expensive problems in clinical research, since roughly four in five trials miss their original recruitment timelines. Predictive recruitment tools use historical enrollment data, site performance records, and patient population modeling to forecast which research sites will hit their targets and which will lag. A CTMS that surfaces these predictions early lets clinical operations managers reallocate effort before a site falls behind, rather than discovering the shortfall at the next monitoring visit. Paired with AI screening that matches eligible participants to the right study, predictive recruitment turns enrollment from a guessing game into a managed forecast. Freeing coordinators from manual chase-down gives them more time for patient care and enrollment.
Cloud-native platforms become the default
Cloud-native research platforms scale to handle clinical studies without new server investments and connect cleanly to electronic data capture feeds. The shift to cloud delivery is nearly complete, with web and cloud-based systems already dominating the CTMS market by delivery mode. Cloud-native research platforms give distributed study teams the same up-to-date information, whether they sit at headquarters or a remote site, and they scale to handle multiple studies without new server investments. Security improves too, since reputable cloud providers maintain certifications and patching cadences that few individual research organizations can match in-house. For sponsors running global trials across jurisdictions, cloud platforms also simplify data residency, letting teams keep clinical data within required regions while preserving a single operational view.
Interoperability standards mature
The final shift is quieter but no less important. As HL7 FHIR adoption widens across the healthcare ecosystem, the barriers between a CTMS, an EDC system, an electronic trial master file, and hospital EHRs keep coming down. Mature interoperability means a patient's data flows from a clinical visit into the study record without manual re-entry, cutting both administrative burden and the human error that re-keying invites. Teams evaluating CTMS platforms now treat standards-based integration as table stakes, because a system that cannot speak FHIR will struggle to connect with the EHRs and devices that increasingly feed modern clinical trials.
Start Building Clinical Research Software with Glorium Technologies
Glorium Technologies has spent over 15 years building healthcare and life sciences software, and that experience shapes how we approach clinical research platforms. A CTMS depends on three things: integration, compliance, and the trust of the people using it. We design for all three from the first discovery session instead of bolting them on later.
Our teams build with HIPAA and GDPR compliance as a baseline, follow HL7 and FHIR standards for interoperability, and connect new systems to the EHR, EDC, and financial tools your operation already runs. Whether you need a custom platform built from scratch or an extension of an existing system, our work spans healthcare software development, custom software engineering, and AI software development for teams adding intelligent automation to recruitment and monitoring.
In one healthcare engagement, we built an at-home fertility testing platform for TurtleHealth.The build included provider portals where clinicians validate generated reports. We also added an order management panel to track devices and critical components across the workflow.
Ready to scope a clinical research management system that fits how your trials actually run? Contact us for an intro call, and we will map the right starting point together.
FAQ
How long does it take to implement a clinical trial management system?
Timelines depend on scope and integrations. A single-site deployment with light customization can go live in a few months, while an enterprise rollout across multiple studies and connected systems often runs six months or longer. The biggest variable is data migration and how cleanly your existing clinical data transfers. Scoping integrations early keeps the project from drifting.
Can a CTMS work for small research sites, or is it only for large sponsors?
Both. Site-level CTMS solutions are built for smaller research operations and tend to focus on patient tracking, scheduling, and site payments. This segment is actually growing faster relative to its size as smaller teams pick up tools once reserved for enterprise sponsors. The key is matching the platform tier to your study volume rather than overbuying.
How does a CTMS support regulatory inspections?
The audit trail does most of the work. Because every record change is timestamped and attributed to a user, you can reconstruct exactly what happened to any patient record or document during an inspection. Built-in reporting also lets you generate compliance documentation on demand instead of assembling it under deadline pressure, which reduces the risk of human error during a high-stakes review.
What is the difference between a CTMS and an EDC system?
They solve different problems. An EDC system captures the clinical data from patient visits, the actual measurements, and outcomes. A CTMS manages the operations around the trial: enrollment status, site performance, budgets, and milestones. Most modern studies run both and integrate them, so operational data and clinical data stay in sync across the study.
How do decentralized trials change CTMS requirements?
Decentralized and hybrid trials pull data from sources a traditional trial never touched, including remote patient monitoring devices, telehealth visits, and patient apps. A CTMS built for this model needs flexible integration and real-time data capture to absorb those feeds without manual re-entry. As the FDA's 2024 guidance pushes decentralized elements further into standard practice, this flexibility is becoming a baseline expectation rather than a premium feature.
Who is a CTMS meant for, and which teams get the most out of it?
A CTMS serves sponsors, CROs, and research sites, but the biggest gains go to teams running more than one straightforward study. A single small trial may not need it. Once you coordinate several protocols, multiple sites, or hybrid visits, the platform earns its place. Operations managers, coordinators, regulatory staff, and finance all work from the same record.
What does a CTMS implementation cover, from timeline to outcome?
Implementation moves through discovery, configuration, integration, data migration, training, and a pilot. A light single-site setup can go live in a few months, while an enterprise rollout often runs six months or more. The result is a working operational hub: live enrollment dashboards, a clean audit trail, payments tied to verified conduct, and on-demand reporting. Data migration usually sets the pace.
What goes into CTMS pricing, and what drives the cost?
The main drivers are licensing or subscription fees, the number of studies and users, integration depth, configuration work, and training. A custom build shifts cost toward engineering hours rather than per-seat licenses. Budget migration and training as separate line items so the total reflects what you will actually spend.
About Hanna Reshetniak